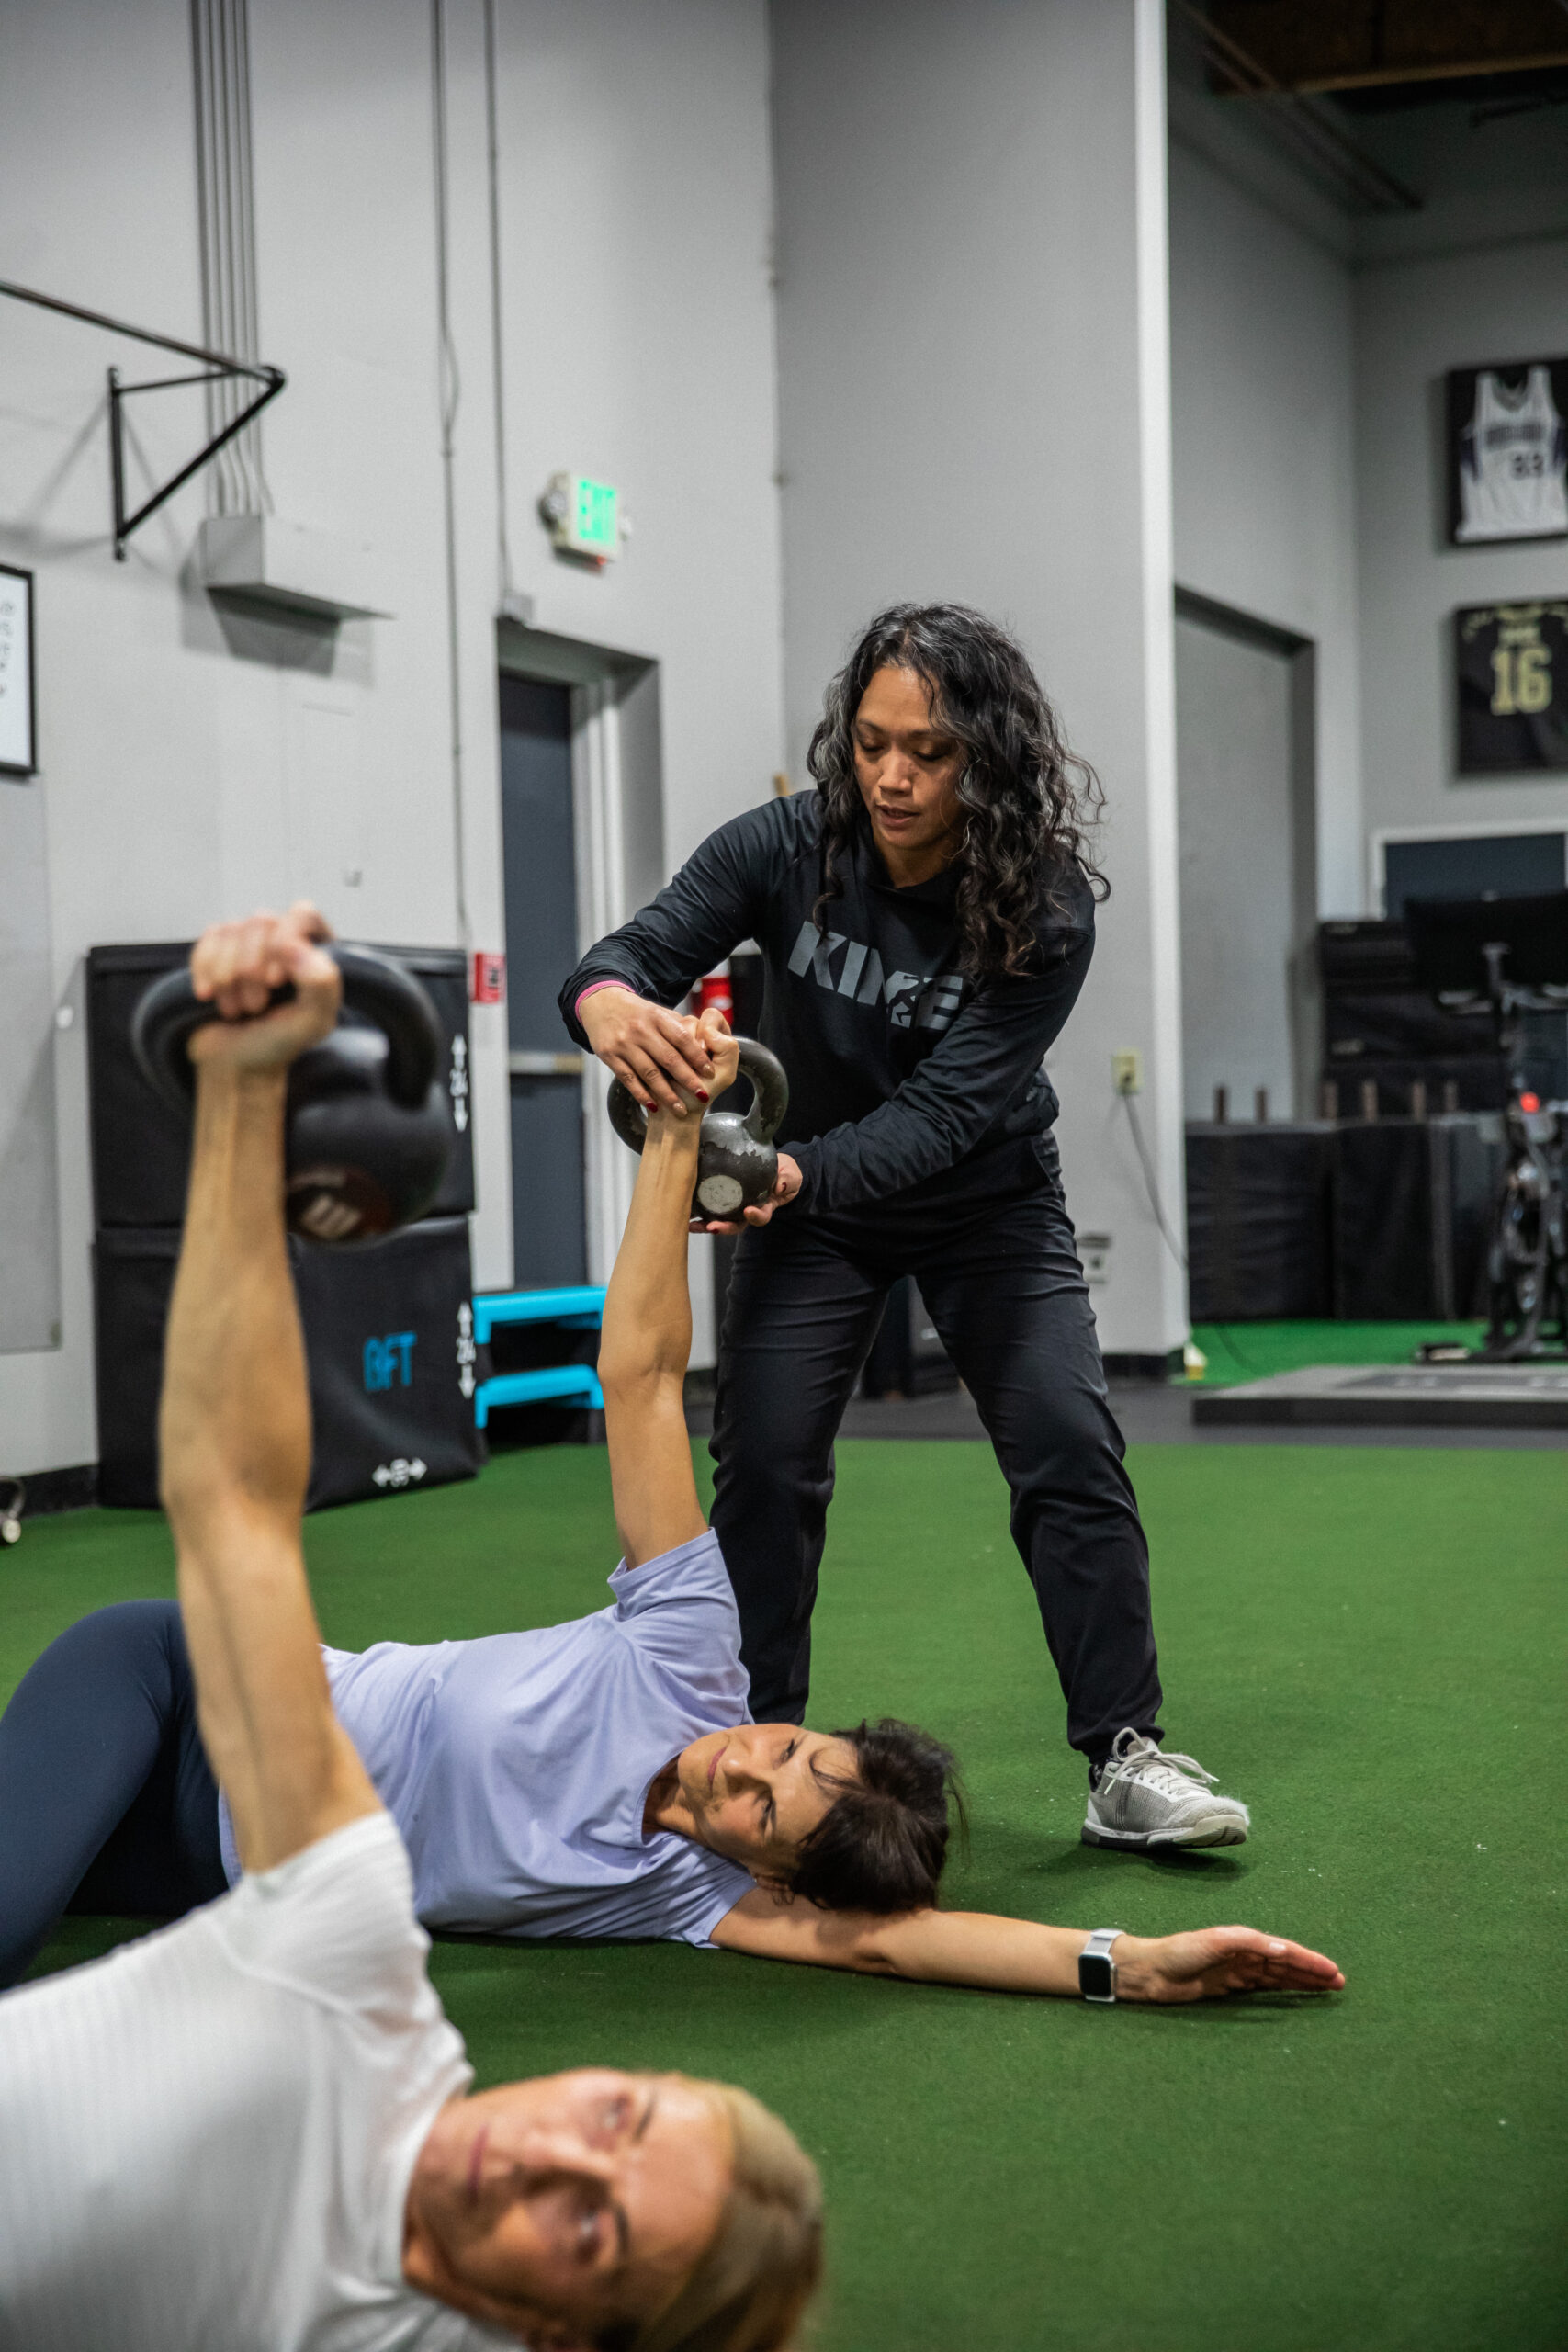The Feedback Loop Is the Skill
Ask a room of clinicians what separates a great one from an average one and you’ll hear the usual answers: hands, eye, experience. But experience is a strange currency. Two clinicians can log the same years and end up in very different places — because experience only compounds when it passes through a feedback loop. Reps without feedback aren’t learning. They’re repetition.
Feedback has a speed limit
Motor learning research has been telling us this for years: feedback changes behavior in proportion to how close it lands to the action. Tell someone what went wrong after the movement is over and you’re asking them to reconstruct a moment that’s already gone. Show them in a mirror and the correction happens while the pattern is still live. Let them feel it — a constraint, a load, a touch cue — and the correction happens below the cognitive layer entirely, at speeds conscious processing can’t touch. The hierarchy matters practically: if your default coaching channel is talking, you’re coaching through the slowest pipe available.
Cue the task, not the anatomy
This is also why body-part cueing underperforms. “Squeeze your shoulder blades” asks the patient to run a movement through conscious anatomical control that no healthy nervous system uses. External cues — push the floor away, reach through the wall, spend less time on the ground — recruit the pattern you want without ever naming it. Better still, choose positions where the pattern is the only way out: a step-up tall enough that the hip has to do the work, a squat taught from the bottom of a box, a drill where losing the counterbalance forces the trunk to organize itself. The position becomes the coach, and the feedback is instant.
The protocol, rehabilitated
School warned most of us off protocols, and the warning had a point: nobody should run every shoulder through the same sheet of exercises. But the opposite of a cookbook isn’t chaos — it’s a controlled experiment. A consistent base routine, applied across a real sample of similar presentations, is the only way you ever find out whether you are the effect. When most of the sample responds, the routine has earned credit. When someone doesn’t, the deviation is diagnostic signal instead of noise. Improvise a new recipe for every patient and you’ve destroyed your own experiment: everyone got something different, some got better, and you learned nothing. The answer was never one protocol. It’s many — indexed to the variables that actually matter — each one a running feedback loop.
Close the loop or don’t call it wisdom
The hardest feedback loop in this profession is the longest one: did it hold? A patient who feels better at discharge and re-injures months later is an outcome most clinicians never see, which means most clinicians are grading themselves on the easy half of the test. Caseload design either protects that follow-up loop or destroys it. Guard it. A clinician early in their career with a fierce feedback loop will pass a veteran who never built one — not eventually, but quickly. The loop is the skill.
These ideas are explored further on KIMEcast Episode 66 Fail Fast. Learn Faster. | The Power of Feedback Loops, the KIME Performance podcast.